Showing posts with label The New England Journal of Medicine. Show all posts

Tuesday, July 30, 2013

Publication Ethics: Unintended consequences of sanctions

The latest changes to US sanctions on Iran, designed to discourage the country from developing nuclear weapons, seem to have caused confusion, leading to some journal editors effectively boycotting research from Iranian medical practitioners and academics.
Regulations set out by the US Office of Foreign Assets Control state that US citizens are authorised to engage in ordinary transactions related to written publications as long as the parties to the transactions are not employed by the Iranian government. Most Iranian universities, hospitals, and research centers are government owned but the regulations specify that the sanctions do not apply to any academic and research institutions or their staff.
Nevertheless, Iranian doctors have told the BMJ that several papers have been refused by journals in the US and Australia in recent months because of the sanctions.
The editor of the Journal of Allergy and Clinical Immunology (JACI), which is owned by Elsevier, explained in an email to an assistant professor in the department of paediatrics at Tehran University of Medical Sciences that the journal could not accept his paper because “US owned journals are unable to handle scientific manuscripts which are authored by Iranian scientists, employed by the Government of Iran.”
Papers from Iranians are also known to have been turned down by the American Journal of Cardiology (also published by Elsevier), the Journal of Ocular Pharmacology and Therapeutics (published in the US by Marie Ann Liebert), and the Australian journal Ophthalmic Epidemiology (published by Informa Healthcare in the UK), all of whom explained that US sanctions prevented them from considering the research.
Dove Medical Press (an open access online publisher whose headquarters are in the UK and editorial office is in New Zealand) turned down a paper saying that “international sanctions currently in place against Iran mean that Dove Medical Press is no longer able to process manuscripts received from Iranian authors.”
“We do not make this decision lightly and have consulted with the authorities both here in New Zealand and in the United Kingdom before making our decision,” said Jeanette Pearce, Dove’s New Zealand based operations manager.
“It is not ethical to treat Iranian researchers this way,” Behrooz Astaneh, acting editor of the Iranian Journal of Medical Science, told the BMJ. “These people want to disseminate data they have obtained in very difficult circumstances because of the sanctions. Research publication should be on merit and have nothing to do with politics.”

Protecting editors

According to a report from Science magazine, Elsevier advised its US editors in April against handling any papers authored by employees of the government of Iran and in an email shown to the BMJ, the editor of JACI explained, “our publisher precludes taking any articles from authors based at Iranian institutions or hospitals.” Yet, Elsevier says it believes in the “free flow of ideas and information as a principle for science and for society” and chief lawyer, Mark Seeley, told the BMJ that the company continues to publish papers from Iranian academics and researchers affiliated with academic or medical institutions. Elsevier decided it was necessary to make “narrowly crafted exceptions” because of the potential for personal liability on the part of its US editors.
Asked if some US editors had possibly misunderstood the publisher’s guidance on this, Seeley responded that the problem was over “the exact definition of ‘government employees’ other than academics and practitioners. Seeley said the company was seeking greater clarity but had not yet received it.
John Sullivan of the US Treasury told the BMJ that “The focus of our sanctions is the Iranian regime and its support for terrorism and its illicit nuclear programme. Our sanctions do not target academic or informational materials.”

A different view

Other American health publications, including the two leading journals the New England Journal of Medicine and Journal of the American Medical Association, said they were continuing to publish Iranian submissions on merit.
“Different journals have adopted very different strategies on this,” Elaheh Malakan Rad, associate professor of paediatric interventional cardiology at the Children’s Medical Centre in Tehran, told the BMJ. “There needs to be clear guidance on the ethical issue here.”
The Committee on Publication Ethics (COPE), which advises editors on handling ethically sensitive issues, discussed problems surrounding Iranian authors in a June meeting and affirmed the need, already previously agreed because of other concerns, that clearer guidance is needed. COPE is planning to add a paragraph to its code of conduct stating that, “Editorial decisions should not be affected by the origins of the manuscript, including the nationality, ethnicity, political beliefs, race, or religion of the authors. Decisions to edit and publish should not be determined by the policies of governments or other agencies outside of the journal itself.”
The United Kingdom government has also changed its sanctions recently and continually updates a list of banned authors and institutions thought to be involved in Iran’s nuclear programme. However, the BMJ continues to take papers on merit and has chosen in some instances to waive the usual author fee charged for open access publication of research because of regulations over bank transactions with Iran.
“The BMJ is against academic boycotts and has no restrictions on publishing articles from authors in Iran,” the BMJ’s editor, Fiona Godlee, said in a statement posted on bmj.com. “We have noted the UK’s restrictions on trading with Iran and are also aware of the new US restrictions. These may have implications for whether we can levy an author fee from an author in Iran. We will decide this on a case by case basis.”
Richard Horton, the editor of the Lancet (which is owned by Elsevier) said: “TheLancet welcomes and encourages research from scientists in all countries, including Iran. Indeed, we are currently working to strengthen our links with Iranian medical and public health scientists.”
by: Sophie Arie
@BMJ

Sunday, July 17, 2011

The Risks and Benefits of 5α-Reductase Inhibitors

Authors : Marc R. Theoret, M.D., Yang-Min Ning, M.D., Ph.D., Jenny J. Zhang, Ph.D., Robert Justice, M.D., Patricia Keegan, M.D., and Richard Pazdur, M.D.
The use of 5α-reductase inhibitors for prevention of prostate cancer continues to be widely discussed within the scientific and medical communities. Much of this discussion has been fueled by the findings of two large randomized, placebo-controlled trials — the Prostate Cancer Prevention Trial (PCPT) with finasteride and the Reduction by Dutasteride of Prostate Cancer Events (REDUCE) trial . Together, these trials showed an overall relative reduction of 23 to 25% in prostate-cancer diagnoses, a seemingly significant benefit from drugs aimed at preventing one of the most common cancers in men. However, the observed reduction resulted from a decreased incidence of only low-grade prostate cancer (Gleason score, ≤6). In fact, in both trials, there was an absolute increase in the incidence of high-grade prostate cancers in the chemoprevention group.
Evaluating the potential chemopreventive benefits of 5α-reductase inhibitors and assessing the potential increased risk for high-grade prostate cancers have been central issues for the Food and Drug Administration (FDA). There has been much hope for an FDA-approved chemopreventive agent for prostate cancer, and there is clearly ongoing off-label use of 5α-reductase inhibitors for this indication. The FDA has been actively evaluating the relevant data and held a meeting of its Oncologic Drugs Advisory Committee to address this topic in December 2010.

Both chemoprevention trials were conducted in men who were at risk for prostate cancer but did not have diagnosed prostate cancer at study entry. The FDA’s analysis of the trials confirmed that there was a relative reduction of approximately 25% in the overall incidence of prostate cancer and a significantly increased incidence of high-grade prostate cancers. During the FDA review of the REDUCE trial, we requested that biopsy specimens be reassessed, according to the modified Gleason scale, by an independent pathologist who was unaware of the earlier scores. The central pathologist for PCPT performed this reassessment. The use of modified Gleason scores is consistent with current recommendations for prostate-cancer grading and the grading system used in PCPT; modified Gleason scores were not originally reported in the REDUCE trial.
The reassessment revealed no reduction in the incidence of tumors with modified Gleason scores between 7 and 10 — a finding that was consistent with the published data. However, an absolute increase of 0.5% in the incidence of tumors with modified Gleason scores of 8 to 10 (relative risk, 2.06; 95% confidence interval [CI], 1.13 to 3.75) was observed with dutasteride treatment. This increase is similar to the absolute increase of 0.7% in the incidence of such tumors observed with finasteride treatment (relative risk, 1.70; 95% CI, 1.23 to 2.34) .These results suggest that one additional man would receive a diagnosis of high-grade prostate cancer (modified Gleason score, 8 to 10) for every 150 to 200 men treated long-term with a 5α-reductase inhibitor.

It has been suggested that detection bias, attributable to the fact that 5α-reductase inhibitors reduce serum levels of prostate-specific antigen (PSA) and prostate volume, led to an increase in detection of high-grade prostate cancer in the finasteride group of the PCPT. Indeed, the sensitivity of an elevated PSA level (a PSA level above 4 ng per milliliter in the placebo group or, in the finasteride group, above the adjusted value designed to correct for a finasteride-induced PSA reduction of approximately 50%) for the detection of prostate cancer, including high-grade tumors, was increased in the finasteride group of the PCPT. The observation that the increased risk of high-grade tumors (modified Gleason score, 8 to 10) with finasteride or dutasteride persisted in analyses of scheduled biopsies independent of PSA results argues against PSA-related detection bias as the cause of the observed increase in the incidence of high-grade tumors. Approximately 56% of all prostate cancers in the PCPT and 90% of those in the REDUCE trial were diagnosed by means of scheduled biopsies.
As for detection bias due to 5α-reductase inhibitors’ reduction of prostate volume by approximately 20%, it is possible that core needle biopsies may uncover more cancers, including high-grade tumors, in smaller prostates because of increased sampling density. Proponents of this hypothesis accounted for the intergroup difference in prostate volume either by statistically adjusting for prostate volume at the time of biopsy (using logistic-regression analysis or the Peters–Belson method) or by circumventing any potential for sampling bias by extrapolating from the Gleason scores for a subgroup of patients who had had prostatectomies to patients without prostatectomy data (weighted imputation estimation). These analyses resulted in estimates of the relative risk of high-grade prostate cancer (Gleason score, 7 to 10) in the finasteride group ranging from no increase to a relative decrease of 27%. Since conventional criteria define “high-grade” as a Gleason score of 8 to 10 and 75% of the increase in tumors with modified Gleason scores of 7 to 10 observed in the finasteride group involved tumors with a score between 8 and 10, the FDA repeated the same analyses, statistically adjusting for prostate volume and using a modified Gleason score of 8 to 10 as the definition of a high-grade tumor. The results of those analyses do not support the contention that increased sampling density is responsible for the increased incidence of high-grade tumors in the finasteride group (see table for opposing risk estimations for tumors with a modified Gleason score of 7 to 10 and those with a score of 8 to 10). Although questions concerning detection bias remain, none of the post hoc exploratory analyses provide convincing evidence that the increased incidence of high-grade disease observed in both trials can be dismissed.
Analyses of these trials indicate that the reduction in prostate-cancer risk with both drugs was limited to tumors with a modified Gleason score of 6 or lower. Prospectively collected data in REDUCE showed that 80% of such tumors met the Epstein pathological criteria for “very-low-risk” disease, which indicates that a reduction in their incidence is unlikely to be clinically significant. An analysis of biopsies performed in response to an elevated PSA level or an abnormal digital rectal examination, as would be done in clinical practice, revealed a smaller reduction in the relative risk of prostate cancer (14%; 95% CI, 4 to 23%) than that reported for all cancers in men receiving finasteride. Therefore, the trade-off inherent in using a 5α-reductase inhibitor for prostate-cancer prevention is the acceptance of one additional high-grade cancer in order to avert three to four potentially clinically relevant lower-grade cancers.

The conclusion drawn by the advisory committee in December was that finasteride and dutasteride do not have a favorable risk–benefit profile for the proposed use of chemoprevention of prostate cancer in healthy men. The FDA agrees with this assessment. The effects of finasteride or dutasteride on the incidence of metastatic prostate cancer and prostate-cancer–specific morbidity and mortality have not been evaluated.
Strategies for reducing cancer risk expose people who do not have and may never develop cancer to a drug and its potential adverse effects. In these circumstances, a high level of certainty about benefits and risks of intervention is warranted. The labels of approved 5α-reductase inhibitors, which are currently indicated for the treatment of symptomatic benign prostatic hyperplasia and male-pattern hair loss, have been modified to include the observation of high-grade prostate cancers in the relevant trials. In addition, health care professionals prescribing 5α-reductase inhibitors to men who opt for PSA screening should be aware that these agents reduce PSA values and that any increase in the PSA level above the lowest value obtained may signal the presence of prostate cancer, even if the value remains in the normal range for men not taking such an agent.

Friday, July 15, 2011

ADT for Prostate Cancer


In the 1990s, reversible androgen suppression with the use of luteinizing hormone–releasing hormone analogues and oral antiandrogen agents was shown to induce apoptotic regression in androgen-responsive cancers, potentially improving the prospects of local control and the duration of survival free of metastatic disease.
Clinical Pearls

How can short-term androgen deprivation be achieved?
In this study, patients assigned to short-term androgen-deprivation therapy (ADT) received flutamide at a dose of 250 mg orally three times a day and either monthly subcutaneous goserelin at a dose of 3.6 mg or intramuscular leuprolide at a dose of 7.5 mg for 4 months.
How more effective was ADT with radiotherapy as compared to radiotherapy alone for patients with localized prostate cancer in this study?
According to the results of this study, the 10-year rate of overall survival was 62% among patients receiving radiotherapy plus short-term ADT (the combined-therapy group) versus 57% among patients receiving radiotherapy alone (hazard ratio for death with radiotherapy alone, 1.17; P=0.03). The addition of short-term ADT was associated with a decrease in the 10-year disease-specific mortality from 8% to 4% (hazard ratio for radiotherapy alone, 1.87; P=0.001).
Morning Report Questions
Q. Which group of patients benefited the most from ADT in this study?
A. The addition of short-term ADT to radiotherapy conferred the greatest clinical benefit in the intermediate-risk subgroup, with an increase in the 10-year rate of overall survival from 54 to 61% and a reduction in the 10-year disease-specific mortality from 10 to 3%.
Q. What are adverse effects of ADT?
A. In prospective studies, short-term ADT caused measurable muscle loss, fat accumulation, decreased insulin sensitivity, and increased cholesterol and triglyceride levels.
@NEJM

Saturday, May 7, 2011

Leukotriene Antagonists as Effective as Other Asthma Therapies?

Leukotriene-receptor antagonists may be as effective as inhaled corticosteroids for first-line treatment of asthma and as effective as long-acting beta agonists for add-on therapy, according to two "real-world" trials reported in the New England Journal of Medicine.
The two trials included individuals aged 12 years and older with asthma. In one, some 300 patients beginning asthma therapy were randomized to open-label treatment with either a leukotriene antagonist or an inhaled glucocorticoid. In the other, roughly 350 patients already taking an inhaled glucocorticoid were randomized to add-on therapy with a leukotriene antagonist or a long-acting beta agonist.
The primary endpoint — asthma-related quality of life at 2 months — was similar between treatment groups. However, the researchers report that at 2 years, outcomes did not quite meet equivalence criteria.
Editorialists note that leukotriene antagonists likely work well in real-world settings because of their ease of use (i.e., pill vs. inhaler).

Wednesday, April 27, 2011

Melanoma : Clinical Pearls and Morning Report Questions

Clinical Pearls


What are the currently approved treatments for metastatic melanoma?
The two therapies approved by the Food and Drug Administration, high-dose interleukin-2 and dacarbazine, are each associated with response rates of only 10 to 20% and a small percentage of complete responses; neither is thought to improve overall survival. In randomized trials, the median survival among patients treated with dacarbazine was less than 8 months.
How prevalent is the v-raf murine sarcoma viral oncogene homologue B1 (BRAF) mutation among patients with metastatic melanoma?
A search for mutations in a component of the MAP kinase pathway in a large panel of common cancers revealed that 40 to 60% of melanomas, and 7 to 8% of all cancers, carry an activating mutation in BRAF.

Morning Report Questions

Q. How effective was the oral inhibitor of BRAF, PLX4032, in treating patients with metastatic melanoma?
A. This trial demonstrated that therapy targeting tumors containing activating V600E BRAF mutations can induce clinically significant tumor regression in patients. PLX4032 induced clinically significant tumor regression in 81% of patients who had melanoma with the V600E BRAF mutation. Responses were observed at all sites of disease, including the bone, liver, and small intestine.
Q. What tumors emerged in patients treated with PLX4032?
A. Eight patients in the dose-escalation cohort (15%) and 10 patients in the extension cohort (31%) developed cutaneous squamous-cell carcinomas — a total of 35 carcinomas. These were reviewed centrally, and all but one either were keratoacanthomas or had features of a keratoacanthoma. The median time to the appearance of a cutaneous squamous-cell carcinoma was 8 weeks; the majority of the carcinomas were resected, and in no case did any lead to discontinuation of treatment.

Monday, October 18, 2010

Regulatory Action on Rosiglitazone


There have been ongoing concerns about the safety of the diabetes drugs containing rosiglitazone (Avandia, Avandaryl, and Avandamet) — a thiazolidinedione antidiabetic agent indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
In 2007, a meta-analysis of controlled clinical trials found increases in the risk of myocardial infarction and a near-significant increased risk of death from cardiovascular causes when rosiglitazone was compared with placebo or with standard diabetes drugs. Following an advisory committee meeting held in July 2007, the U.S. Food and Drug Administration (FDA) added information about the possibility of ischemic cardiovascular risk to the drug’s existing boxed warning. At the same time, the FDA also required the sponsors to conduct a head-to-head cardiovascular safety trial of rosiglitazone versus pioglitazone — the other antidiabetic drug in this class available in the United States. After new data became available, the FDA held a second advisory committee meeting on rosiglitazone safety on July 13 and 14, 2010. On September 23, 2010, the FDA announced regulatory actions stemming from these deliberations.
The FDA is restricting access to rosiglitazone by requiring the drug sponsor to submit a Risk Evaluation and Mitigation Strategy, or REMS. Under the Food and Drug Administration Amendments Act of 2007, the FDA can require a drug sponsor to issue a REMS to impose certain restrictions so that the benefits of a drug continue to outweigh its risks. When the REMS for rosiglitazone is implemented, the drug will be available to patients not already taking it only if they are unable to achieve glycemic control using other medications and, in consultation with their health care professional, decide not to take pioglitazone for medical reasons. Current users of rosiglitazone will be able to continue using the medication if they appear to be benefiting from it and they acknowledge that they understand these risks. Doctors will have to attest to and document their patients’ eligibility; patients will have to review statements describing the cardiovascular safety concerns. The agency anticipates that the REMS will limit use of rosiglitazone significantly.
The FDA is taking this step on the basis of its assessment of all available data on the cardiovascular ischemic risk of rosiglitazone. At the recent advisory committee meeting, FDA scientists and external experts presented new signals of risk from observational studies and meta-analyses. Each of these data sources has its limitations, including the potential for bias in observational studies and the fact that pooling the results of the studies that were not designed to assess cardiovascular risk can lead to invalid conclusions. But there was no reliable evidence to refute these cardiovascular safety concerns.
After considering the data, 18 members of the advisory committee found significant cause for concern about an increase in ischemic cardiovascular events with rosiglitazone relative to other non-thiazolidinedione antidiabetic agents, whereas 6 committee members did not. Twenty-one members believed that the cardiovascular risk with rosiglitazone was significant as compared with pioglitazone. Three members did not reach this conclusion. This 21-to-3 vote also reflected recognition that available evidence on pioglitazone, including the results of a well-designed trial in high-risk patients, does not show a signal of a cardiovascular ischemic risk.
The rosiglitazone controversy is remarkable because there are strongly held, differing positions on how the agency should respond to emerging safety data, both inside the FDA and in the biomedical community. The 2010 advisory committee was split in advising the agency about what to do. Moving from the least to most restrictive options, 3 members voted to allow continued marketing with no changes to the label; 7 voted that the FDA should adjust the label to account for the new concerns but take no additional action; 10 members voted for the FDA to both increase warnings and limit access to rosiglitazone; and 12 voted that the medication should be removed from the market altogether. The FDA decided to increase warnings and limit access to rosiglitazone substantially.
The FDA anticipates questions on whether the agency has gone too far, or not far enough.
Some may note the limitations of available data and argue that the FDA should provide more information to clinicians but not impose additional restrictions. The FDA’s response is that a label change alone does not provide adequate assurance that use of rosiglitazone will be limited to appropriate patients. New label warnings are not always read. The significant questions about the drug’s cardiovascular safety justify stronger measures to support good clinical decision making and protect patients.
Others may argue that rosiglitazone should be removed from the market because there is no predefined patient population for whom it is known that it will be more advantageous than pioglitazone. Our response starts with the fact that rosiglitazone does have benefits in glycemic control. These benefits include reductions in short-term complications of hyperglycemia. There is also a broad range of evidence supporting glycemic control as a reliable surrogate marker for decreasing the rate of progression of the microvascular complications of diabetes, including retinopathy and kidney disease.
Against these benefits, we must assess the evidence of rosiglitazone’s cardiovascular risks. This evidence is concerning, but it is not definitive. There are patients with severe type 2 diabetes whose disease may not be controlled on other medications and either may not tolerate pioglitazone or, in consultation with their health care professional, decide not to take pioglitazone for other medical reasons. If well informed, these patients may be willing to accept the concern about cardiovascular safety in exchange for the known benefits of glycemic control. The FDA recently announced that the agency is investigating further signals of a possible increase in the risk of bladder cancer with long-term use of pioglitazone. Although the absolute risk to all patients appears to be small, some patients with a history of bladder cancer, in consultation with their doctors, may decide not to take pioglitazone. When there are just two drugs in a class, and many outstanding uncertainties, maintaining some flexibility may have value for patient care.
The FDA will continue to review emerging data on rosiglitazone. The agency is requiring an independent readjudication of end points at the patient level of an important trial of rosiglitazone’s safety — the Rosiglitazone Evaluated for Cardiovascular Outcomes in Oral Agent Combination Therapy for Type 2 Diabetes, or RECORD, trial. As published, RECORD demonstrated the noninferiority of rosiglitazone when compared with sulfonylureas and metformin with respect to a composite end point of multiple cardiovascular events and death, but it did not rule out an elevated risk of myocardial infarction. However, during the course of the FDA’s review of the RECORD study, serious questions arose about potential bias in identification of cardiovascular events arising from the study’s open-label design. The FDA is requiring the readjudication of end points to provide additional clarity about the findings.
Other actions taken by the agency include the discontinuation of the trial known as TIDE (Thiazolidinedione Intervention with Vitamin D Evaluation) — the head-to-head cardiovascular safety trial of rosiglitazone versus pioglitazone. Given the current state of the evidence and the FDA’s recent actions, participants would need to be informed of significant concerns that rosiglitazone may cause more cardiovascular disease than pioglitazone, the restrictions on the use of rosiglitazone that will be imposed through the REMS, and that it is unlikely that, outside the study, the patient would receive rosiglitazone. According to recent recommendations from an Institute of Medicine committee, such an informed consent process might be justified if the study’s outcome could realistically yield a significant benefit to public health. At this point, however, the FDA does not consider TIDE such a study. It is possible that additional data, including information from the readjudication of RECORD, could support additional clinical trials of rosiglitazone safety.
How can the FDA prevent such uncertainty about a major risk from happening again? In 2008, the FDA issued draft guidance on the assessment of cardiovascular risk for new antidiabetic drugs. In this guidance, the FDA proposed upper boundaries for the risk of major cardiovascular events in a meta-analysis or a noninferiority study that compares the new drug with standard therapy. The FDA also recommends that the data for these comparisons come from longer-term trials — that is, trials of at least 2 years’ duration. Guidance represents the FDA’s current thinking on how to meet a specific requirement — in this case, demonstration of the safety of a new drug for this indication. Drug sponsors are free to use other methods to show safety, but such methods need to be equally robust. The expectation of longer-term evidence on the cardiovascular risks of new antidiabetic drugs will assure that such evaluations are routinely conducted and that longer-term data on multiple safety parameters are also available.
The case of rosiglitazone underscores the need for a robust evidence base to demonstrate the safety of medicines administered long-term. The FDA is committed to advancing the science of drug safety evaluation, during both drug development and in the postmarketing period.

Friday, August 13, 2010

Invasive Coronary Angiography vs Coronary CTA


Borrowing a technique from the virtual colonoscopy playbook, researchers from South Carolina and Germany found that coronary CT angiography (CTA) is better than previously thought compared to catheter-based coronary angiography -- in fact the two tests are essentially equivalent, they said.
The comparison was obtained following the development of an enhanced reference standard known as segmental unblinding, which compares the results of two tests to each other rather than to a so-called "gold standard" modality -- which often tends to be at least slightly tarnished.
Perhaps the biggest problem with gold standard tests -- whether used for optical colonoscopy, catheter angiography, or any other exam -- is that they inherently limit the success of any new test to which they're compared, said U. The study was presented last month at the 2010 Society of Cardiovascular Computed Tomography meeting (SCCT) in Las Vegas.
"Whatever results you accomplish with the newer test, the best possibility is that it is as good as the traditional test, but it can never be better and typically it's worse than the traditional test in your analysis," said Schoepf, who is a professor of medicine and radiology at the Medical University of South Carolina (MUSC) in Charleston.
Principal investigator Matt Kerl, MD, along with Schoepf and colleagues, followed almost exactly the segmental unblinding method used by Pickhardt et al in their landmark 2003 virtual colonoscopy trial (New England Journal of Medicine, December 4, 2003, Vol. 349:23, pp. 2191-2220).

The essential difference was the group's focus on coronary artery segments rather than colon segments.
Pickhardt and colleagues used optical colonoscopy followed by virtual colonoscopy (also known as CT colonography or CTC). But instead of simply comparing the virtual colonoscopy results to optical colonoscopy and expressing the VC sensitivity as a percentage of the optical colonoscopy sensitivity, the researchers took the extra step of doing the comparison in reverse.
In other words, after the colonoscopy interpretation, they went back to compare VC to the colonoscopy results, pointing out apparent lesions optical colonoscopy may have missed and enabling the gastroenterologists to recheck those segments for possible missed lesions. The resulting enhanced gold standard was a fairer comparison of the techniques, delivering for VC higher sensitivity compared to conventional colonoscopy than it would otherwise have achieved.
In the cardiac study from MUSC and the University of Frankfurt, the researchers followed the same method but with coronary artery segments, Schoepf said.
"We had two cardiologists interpret those catheter angiographies blinded, then based on result of coronary CT angiography, we alerted those same interpreters to areas that looked funny on CTA -- and we asked them to have a second look to see if there was something they had missed. And that was indeed so in a number of cases," Schoepf said.
The researchers from MUSC and the University of Frankfurt prospectively compared the per-segment and per-patient accuracy of coronary CTA and invasive coronary angiography (ICA) for diagnosing significant stenosis using composite findings from both tests as an enhanced reference standard.
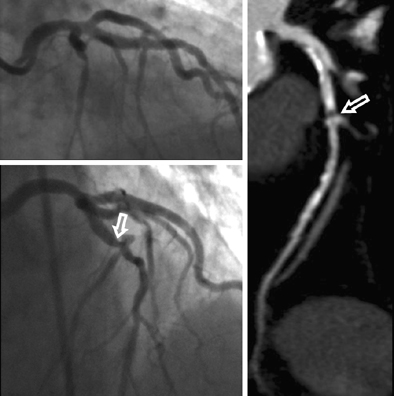
A total of 113 patients underwent both coronary CTA and invasive angiography, and the researchers assessed the per-segment and per-patient accuracy of coronary CTA compared with initial angiography interpretation. Angiographers were then unblinded to the coronary CTA results to re-evaluate angiography with knowledge of the coronary CTA findings -- the enhanced reference standard.
Using the enhanced reference standard instead of the initial angiography interpretation alone, accuracy of coronary CTA for identifying segments (patients) with 50% or greater stenosis increased from 97.7% (96.5%) to 98.1% (98.2%).
Per-segment/per-patient sensitivity rose from 90.5% (100%) to 90.8% (100%), and per-segment/per-patient specificity increased from 98.4% (94.3%) to 98.9% (97.1%).
Coronary CTA found six segments and two patients with stenoses of 50% or greater that had been missed on initial angiography. The diagnostic accuracy between the tests was not significantly different (p = 0.87).
Using the enhanced referenced standard shows that "these two tests are not that much different," Schoepf said. The results convey a couple of messages about the tests, he said.
"Catheter angiography is a good gold standard, but it may not be the best because of limitations this test has which we all know about," Schoepf said. For one thing, angiography has trouble depicting a key coronary artery, the left main, because it's typically tortuous and complex anatomy is not well-suited to catheterization.
A current article in Circulation describes problems with the projection angles in catheter angiography, Schoepf said. Depending on the angle, a minor slit stenosis can appear quite significant at angiography, leading to false positives and potentially needless intervention.
"If you take vertical projection images of that it may look perfectly fine, but if you're angulated by 90°, you see a significant stenosis all of the sudden," he said.
Of course, coronary CTA has its own limitations, which include difficulty visualizing the smallest and most distal lesions. But the take-home message for the study is that nothing beats the power of an enhanced gold standard, Schoepf said.
"What we recommend is that people abandon the idea of using catheter angiography as the gold standard for measuring the performance of coronary CTA because of the known limitations that are inherent to catheter angiography," he said. "Approaches such as ours -- which create more-independent reference standards by combining results from both tests -- may be more valuable and accurate in describing the performance of a test."


By : Eric Barnes 

Image :Invasive coronary angiography and coronary CTA studies in a 62-year-old woman. Significant stenosis of the mid left anterior descending coronary artery (arrows) just proximal to the second diagonal branch was missed during initial interpretation of invasive coronary angiograms (upper left) due to superimposition of vessels. The lesion was detected on coronary CTA, displayed as curved multiplanar reformat (right). Re-evaluation of invasive coronary angiography (lower left) after unblinding of coronary CTA results confirms lesion in a single angiographic projection. Images courtesy of Matt Kerl, MD, and U. Joseph Schoepf, MD.


Sunday, July 4, 2010

Benign Paroxysmal Positional Vertigo


Benign paroxysmal positional vertigo is a common peripheral vestibular disorder. It is caused by loose otoconia, which detach from the utricular macula and fall into any one of the three semicircular canals. Patients report brief episodes of rotary vertigo triggered by changes in head position. The most common form of the disorder affects the posterior semicircular canal and is diagnosed with the Dix–Hallpike maneuver. A positive Dix–Hallpike test is manifested as upbeating torsional nystagmus with a fast component that rotates toward the undermost ear. This nystagmus may be seen with the unaided eye but is often more pronounced if fixation is eliminated with the use of Frenzel lenses or video-oculography goggles. Treatment of benign paroxysmal positional vertigo is directed at returning the displaced otoconia to their proper location in the inner ear. Various effective particle-repositioning maneuvers have been developed and are curative in most cases.

video:positive Dix-Hallpike test

@NEJM

Tuesday, June 8, 2010

Parkinson's Disease : Pallidal vs Subthalamic Stimulation


an interesting study about Parkinson's disease management;comparison of Pallidal and Subthalamic stimulation published in New England Journal of Medicine.

Background:
Deep-brain stimulation is the surgical procedure of choice for patients with advanced Parkinson's disease.The globus pallidus interna and the subthalamic nucleus are accepted targets for this procedure .In this study the 24 month outcomes for two groups of patients undergone two procedures are comapred:patients who had undergone bilateral stimulation of the globus pallidus interna (pallidal stimulation) or subthalamic nucleus(subthalamic stimulation).


299 patients with idiopathic parkinson's disease were randomly assigned to undergo either pallidal stimulation(152) or subthalamic stimulation (147).The primary outcome ws the change in motor function,as blindly assessed on the Unified Parkinson's Disease Rating Scale,part III(UPDRS-III),while patients were recieving but not recieving antiparkinsonian medication.Secondary outcomes included self-reported function ,quality of life ,neurocognitive function,and adverse events.

Results:
Mean changes in the primary outcome did not differ significantly between the two study groups(P=0.50).There was also no significant difference in self-reported function.Patients undergoing subthalamic stimulation required a lower dose of dopaminergic agents than did  those undergoing pallidal stimulation(P=0.02).One component of processing speed(visumotor)declined more after subthalamic stimulation than after pallidal stimulation(P=0,03).The level of depression worsened after subthalamic stimulation and improved after pallidal stimulation(P=0.02).Serious adverse events occured in 51% of patients undergoing pallidal stimulation and in 56% of those undergoing subthalamic stimulation ,with no significant between-group differences at 24 months.

Conclusions:
patients with Parkinson' disease had similar improvement in motor function after either pallidal or subthalamic stimulation .Nonmotor factors may reasonably be included in the selection of surgical target for deep-brain stimulation .

Sunday, May 30, 2010

Target Ranges of Oxygen Saturation in Extremely Preterm Infants


Previous studies have suggested that the incidence of retinopathy is lower in preterm infants with exposure to reduced levels of oxygenation than in those exposed to higher levels of oxygenation. However, it is unclear what range of oxygen saturation is appropriate to minimize retinopathy without increasing adverse outcomes.
Methods We performed a randomized trial with a 2-by-2 factorial design to compare target ranges of oxygen saturation of 85 to 89% or 91 to 95% among 1316 infants who were born between 24weeks 0 days and 27 weeks 6 days of gestation. The primary outcome was a composite of severe retinopathy of prematurity (defined as the presence of threshold retinopathy, the need for surgicalophthalmologic intervention, or the use of bevacizumab), death before discharge from the hospital, or both. All infants were also randomly assigned to continuous positive airway pressure or intubation and surfactant.
Results The rates of severe retinopathy or death did not differ significantly between the lower-oxygen-saturation group and the higher-oxygen-saturation group (28.3% and 32.1%, respectively; relative risk with lower oxygen saturation, 0.90; 95% confidence interval [CI], 0.76 to 1.06; P=0.21). Death before discharge occurred more frequently in the lower-oxygen-saturation group (in 19.9% of infants vs. 16.2%; relative risk, 1.27; 95% CI, 1.01 to 1.60; P=0.04), whereas severe retinopathy among survivors occurred less often in this group (8.6% vs. 17.9%; relative risk, 0.52; 95% CI, 0.37 to 0.73; P<0.001). There were no significant differences in the rates of other adverse events.
Conclusions A lower target range of oxygenation (85 to 89%), as compared with a higher range (91 to 95%), did not significantly decrease the composite outcome of severe retinopathy or death, but it resulted in an increase in mortality and a substantial decrease in severe retinopathy among survivors. The increase in mortality is a major concern, since a lower target range of oxygen saturation is increasingly being advocated to prevent retinopathy of prematurity.


                                   @NEJM
 SUPPORT Study Group of the Eunice Kennedy Shriver NICHD Neonatal Research Network

Friday, January 8, 2010

The Mystery Of Painful Purple Toes

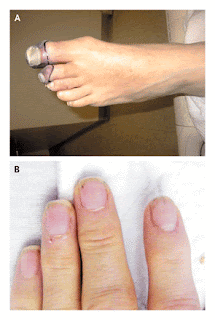
A 57-year-old man presented to the emergency department with painful purple toes. On the day of presentation, he had first been seen in another hospital but left against medical advice before the evaluation was complete. He had first noted a painful discoloration of his left great toe 2 weeks earlier. The pain and discoloration progressed to involve the left second and third toes (Figure 1A). During the 3 weeks preceding presentation, the patient also had intermittent blurry vision, intermittent chest pain, fatigue, anorexia, drenching night sweats, and a weight loss of 6.8 kg (15 lb). His roommate commented that thepatient had also been slightly confused.


Fig1A,B

This patient's painful purple toes are suggestive of peripheral arterial ischemia. The differential diagnosis includes arterial thromboembolism resulting from a hypercoagulable state or from disseminated intravascular coagulation, perhaps related to cancer; embolus of infectious or thrombotic material from endocarditis; paradoxical embolus through an intracardiac shunt; precipitation of cryoglobulins; small-vessel vasculitis; and secondary vasculitis from an underlying connective-tissue disease, such as systemic lupus erythematosus. The possibility of cholesterol emboli should also be considered, particularly in patients who have aortic aneurysms or who have recently undergone vascular procedures. Thromboangiitis obliterans, or Buerger's disease, would be a consideration if the patient smokes. His history suggests at least two and perhaps three separate vascular events in the left foot, serially affecting the digital arteries of the great, second, and third toes. Combined with the report of blurry vision and confusion, the patient's history raises the possibility that a central vascular process is affecting the peripheral and cerebral circulatory beds. The intermittent nature of the chest pain and visual symptoms suggests the possibility of sporadic emboli. Finally, the night sweats, fevers, and weight loss point to a systemic illness, such as infection, cancer, or connective-tissue disease. Specific points to review include risk factors for subacute bacterial endocarditis, such as injection-drug use, and risk factors for hypercoaguable states, such as a family history. Further history taking and physical examination should be performed to seek evidence of hypercoagulability or a systemic illness, such as endocarditis, cancer, or vasculitis.


The patient had a history of hypertension, anxiety, chronic back pain, and gastroesophageal reflux disease. While in the Marine Corps in Vietnam, he had malaria and injuries to the hip and skull. Since serving in Vietnam he had also had post-traumatic stress disorder. Two years before presentation, a screening colonoscopy detected benign polyps. His medications included alprazolam, oxycodone with acetaminophen, and esomeprazole. The patient worked for the U.S. Postal Service and was living with a friend. He reported smoking half a pack of cigarettes daily for 30 years, weekly alcohol use, and rare but ongoing intranasal cocaine use, but no intravenous drug use. He was divorced and had not recently been sexually active. There was no family history of cancer, autoimmune diseases, diabetes, or clotting disorders.
Smoking increases the risks of several cancers, including lung and pancreatic cancers, which may in turn induce a hypercoaguable state. Intranasal cocaine use can cause vasospasm, which may exacerbate digital ischemia, and is also associated with otherbehaviors that are predisposing factors for hepatitis C, a common cause of cryoglobulinemia, and acquisition of the human immunodeficiency virus (HIV). Suspicion of limb ischemia, in addition to prompting an evaluation for physical findings indicative of such systemic disease processes, calls for a thorough examination of the peripheral pulses and may warrant consultation with a vascular surgeon.
On physical examination, the patient's temperature was 36.4°C; pulse, 104 beats per minute; blood pressure, 167/86 mm Hg; respiratory rate, 14 breaths per minute; and oxygen saturation, 96% while he was breathing ambient air. No Roth's spots were seen on funduscopy. The carotid pulses were normal, without bruits, and the chest was clear on auscultation. Cardiac examination revealed a normal S1 sound and a physiologically split S2 sound, without a murmur or rub, and the presence of an S4 gallop. The abdomen was not tender, and neither the liver nor the spleen was enlarged. There was no lymphadenopathy or thrush. The dorsalis pedis and posterior tibialis pulses in the left foot were diminished but palpable, and the foot was warm. On each of the first three toes of the left foot there was a well-demarcated, cool, tender area of nonblanching, dark-purple discoloration. Capillary refill in the unaffected toes was normal. There was no rash, edema, or livedo reticularis of the legs. Distal splinter hemorrhages were noted in several fingernails (Figure 1B). There were no Janeway's lesions or Osler's nodes. Neurologic examination revealed a deficit in the left visual field. The patient received a score of 29 points out of 30 on the Mini–Mental State Examination, having difficulty only when attempting to repeat the phrase, "no ifs, ands, or buts."
The white-cell count was 15,510 per cubic millimeter, with 80% granulocytes, 14% lymphocytes, 5% monocytes, and 1% eosinophils. The hemoglobin and platelet counts were normal, and the erythrocyte sedimentation rate was 19 mm per hour. Levels of electrolytes, blood urea nitrogen, creatinine, albumin, and globulin were normal. The level of C-reactive protein was 32.1 mg per liter (reference range, 1.0 to 3.0). The serum level of creatine kinase was 40 U per liter (reference range, 41 to 266); creatine kinase MB, 2.7 ng per milliliter (reference value, <5.0);> I, 2.22 ng per milliliter (reference value, <0.04).> normalized ratio for the prothrombin time was 1.1, the partialthromboplastin time 25.7 seconds (reference range, 23.8 to 36.6), and the fibrinogen level 264 mg per deciliter (reference range, 200 to 450). A blood smear showed hypochromia; no schistocytes were identified. An electrocardiogram showed a normal sinus rhythm with ST-segment elevations in the inferior and anteroseptal leads.

The finding of a well-demarcated, discolored area on each of the three toes of the left foot supports the possibility of a separate embolus to each of the three small digital arteries feeding the affected toes, rather than a single, more proximal thrombotic or embolic event. The lesions are consistent with localized ischemia, infarction, or thromboangiitis obliterans, but the fact that the foot is warm, with palpable pulses, rules out critical limb ischemia. Although the findings on physical examination do not rule out the possibility of a small-vessel vasculitis, the absence of livedo reticularis makes the presence of cholesterol emboli unlikely. The splinter hemorrhages are consistent with systemic emboli, but these hemorrhages are a nonspecific finding that can also be associated with nail trauma, autoimmune disease, connective-tissue disease, cancer, or endocarditis. Splinter hemorrhages are more specific for subacute bacterial endocarditis when they are present in the proximal, rather than distal, nail plate.
The elevated white-cell count suggests infection, but it is a nonspecific finding. The normal coagulation studies and absence of schistocytes on the blood smear are not consistent with a diagnosis of disseminated intravascular coagulation. The combination of the elevated level of troponin I and the ST-segment abnormalities raises the possibility of an acute coronary syndrome, although the apparent involvement of two vascular territories (right and left anterior descending coronary arteries) on electrocardiography and evidence of ischemia elsewhere make emboli to the coronary circulation seem more likely. Echocardiography might identify a cardiac source of emboli and would help to gauge the extent of myocardial injury. Brain imaging is warranted to evaluate the cause of the patient's visual field deficit and slightly altered mental status.


Magnetic resonance imaging (MRI) of the brain ), including diffusion-weighted imaging, revealed multiple small lesions in the right temporal and occipital lobes, right thalamus, both parietal lobes, left frontal lobe, and both cerebellar hemispheres; there was also a large area of enhancement in the right occipital and parietal lobes. Magnetic resonance angiography of the head and neck showed decreased blood flow in the posterior communicating artery (Fig2A,B). A transthoracic echocardiogram showed a mildly thickened mitral valve, with mild regurgitation, and structurally normal aortic, tricuspid, and pulmonary valves. The left ventricular ejection fraction was normal, and therewere no abnormalities in wall motion. The results of venous ultrasonography and computed tomographic (CT) pulmonary angiography performed at the other hospital were obtained; they showed thrombi in the great saphenous veins of both legs and a small pulmonary embolus in the lower lobe of the right lung.
Fig-2A,B

The MRI findings are consistent with embolic disease of the brain, with the emboli mostly likely traveling through both the carotid and vertebrobasilar arteries from the left heart or proximal aorta. The disease process is not limited to the arterial circulation, as evidenced by the pulmonary embolus and venous thrombi of the legs. Further evaluation should focus on identifying a disease process that would explain both the venous and the arterial thrombosis, including evaluation for an underlying hypercoaguable state. Paradoxical embolism from a venous source, passing through an intracardiac shunt, could also explain the presence of both arterial and venous lesions. Although the transthoracic echocardiogram showed no evidence of a shunt, studies performed without the injection of agitated saline, such as this one, have a low sensitivity for atrial septal defects. Because of the high clinical suspicion for subacute bacterial endocarditis, further evaluation with transesophageal echocardiography is appropriate. Empiric antibiotic treatment should be initiated after blood cultures are obtained.
Emergency cardiac catheterization warrants consideration in any patient with ST-segment elevations, but in this case the normal ventricular wall motion on the echocardiogram, the presence of ST-segment abnormalities in two distinct vascular distributions, and the absence of ongoing chest pain all favor coronary emboli as the cause of the patient's symptoms and elevated troponin levels. Cerebral emboli are associated with a risk of hemorrhage, particularly if they are infectious, which in turn increases the risk of systemic anticoagulation, in addition to the anticoagulation that would be required with a percutaneous intervention performed at cardiac catheterization.
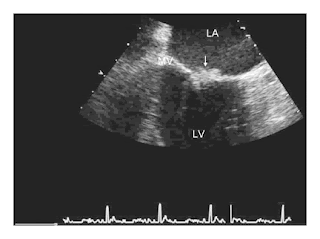
Anticoagulant therapy was deferred pending further evaluation. A transesophageal echocardiogram showed a 7-mm mobile echodensity on the atrial aspect of the posterior mitral-valve leaflet, with no evidence of perivalvular abscess or leaflet perforation, and mild-to-moderate mitral regurgitation (Figure 3). Treatment with ceftriaxone, vancomycin, and gentamicin was initiated for presumed infective endocarditis. However, multiple blood cultures — including cultures grown from samples obtained before antibiotic therapy was begun, cultures held for 2 weeks, and fungal blood cultures — were all negative. Serologic tests for HIV, coxiella, bartonella, treponema, and hepatitis B virus were negative. Serum hepatitis C virus RNA was undetectable.


Fig3- Transesophageal Echocardiogram
A midesophageal commissural view of the mitral valve shows the lesion (arrow). LA denotes left atrium, LV left ventricle, and MV mitral valve.

The negative results of tests for infection increase my suspicion that the causes of the cardiac valvular vegetations and thromboembolic disease are noninfectious. Nonbacterial thrombotic endocarditis (commonly known as marantic endocarditis) is a potential complication of connective-tissue diseases and cancer, either of which could explain the patient's weight loss and night sweats, and may also be associated with concurrent venous and arterial thromboembolism. Further studies should include assays for the lupus anticoagulant and anticardiolipin antibodies, since the antiphospholipid-antibody syndrome could explain the valvular lesion and the venous and arterial thromboses. In the absence of localizing symptoms, imaging of the abdomen and pelvis should be considered to look for evidence of cancer.
Anticardiolipin antibodies were not detected, and a test for lupus anticoagulant was negative. CT of the abdomen revealed multiple low-attenuation lesions in the liver, a finding suggestive of metastatic disease, as well as a small low-attenuation lesion in the head of the pancreas, an enlarged gastrohepatic lymph node, and bilateral wedge-shaped renal infarcts (Figure 4). CT-guided fine-needle aspiration of a liver lesion was performed, and cytologic examination of the aspirate revealed a poorly differentiated adenocarcinoma of undetermined primary origin (Figure 5). Serum levels of alpha-fetoprotein and prostate-specific antigen were normal. The level for the beta subunit of human chorionic gonadotropin was 20 mIU per milliliter (reference range, ≤1.5), and that for carcinoembryonic antigen was 4.7 ng per milliliter (reference range, ≤2.5). The serum level of the carbohydrate antigen 19-9 (CA 19-9) was 16,611 U per liter (reference value, <35).
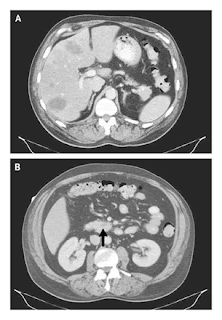


Fig4-Contrast Enhanced CT of the Abdomen
Multiple low-attenuation lesions can be seen in the liver (Panel A), and a small low-attenuation lesion is visible in the head of the pancreas (Panel B, arrow)

Figure 5


Figure 5.-Specimen from Fine-Needle Aspiration of a Liver Lesion.
Staining of the aspirate with hematoxylin and eosin shows sheets of poorly differentiated malignant cells (Panel A) and the mitotic figures and abundant clear cytoplasm that are consistent with adenocarcinoma (Panel B).


Although measurement of the CA 19-9 level should not be used as a screening test for pancreatic cancer in the general population because of its very low positive predictive value, in a patient with a pancreatic mass and suggestive clinical findings, such as this patient, a positive test result strongly supports a diagnosis of pancreatic carcinoma. Slight elevations in the levels of human chorionic gonadotropin and carcinoembryonic antigen are nonspecific and can be seen in pancreatic cancer, especially when it has metastasized to the liver. The identification of metastatic adenocarcinoma confirms the diagnosis of nonbacterial thrombotic endocarditis associated with cancer. Although concurrent arterial and venous thromboemboli are a rare complication of cancer, they are more common in cases of nonbacterial thrombotic endocarditis, as was true with this patient. Anticoagulant therapy with unfractionated heparin should be initiated to decrease the risk of recurrent thromboembolism.
Treatment with unfractionated heparin was initiated on hospital day 8; the regimen was subsequently changed to low-molecular-weight heparin. Over the course of the next week, progressive renal insufficiency, visual impairment, and episodes of psychosis with flashbacks to the Vietnam War developed. Plans for chemotherapy were deferred because of progressive multiorgan dysfunction and the poor prognosis, even with treatment. The patient requested transition to palliative care, and he died within weeks after his initial presentation. A postmortem examination was not performed.
Commentary
This patient's evaluation reveals how a careful history taking and a broad consideration of the possible causes of seemingly disparate events — including limb ischemia, blurred vision, chest pain, and weight loss — can lead to the unifying diagnosis of a systemic condition. The patient's history, the findings on physical examination, and the radiologic studies prompted consideration of a source of systemic emboli and the initiation of empirical therapy for infective endocarditis while an evaluation for noninfectious causes was performed. A key feature of this case was the presence of concurrent arterial and venous thromboemboli, which can be attributed to only a small number of unifying diagnoses.

Once a cardiac valvular mass was discovered, the clinicians chose to delay the use of systemic anticoagulation because of the risk of intracerebral hemorrhage. There is considerable controversy regarding the risk of hemorrhage when a patient has intracranial infective emboli. Some retrospective studies have shown a high risk of intracranial hemorrhage among patients with infective endocarditis and cerebral infarction who undergo anticoagulant treatment for cardiopulmonary bypass, whereas others have not. In this case, since the patient's blood cultures remained negative and radiologic imaging suggested disease that had metastasized to the liver, it became clear that nonbacterial thrombotic endocarditis was the likely diagnosis. Although the use of anticoagulation with heparin in the treatment of nonbacterial thrombotic endocarditis has not been studied in a randomized trial, it is thought to be beneficial, especially in cases that arise as a consequence of a malignant disease, and it does not seem to increase the risk of hemorrhage in association with cerebral emboli.
The prevalence of nonbacterial thrombotic endocarditis on autopsy ranges from 0.3% to 9.3%, depending on sample preparation and the prevalence of malignant disease in the source population. Although nonbacterial thrombotic endocarditis has been reported in neonates and children, frequently in association with congenital heart disease, it is most common in patients 40 years of age or older.In adults, it is often associated with cancer, but it has also been reported in association with systemic lupuserythematosus, burns, HIV infection, tuberculosis, uremia, radiation exposure, snakebites, and trauma from pulmonary catheters.When malignant disease is present, adenocarcinoma of the pancreas is cited as the most common primary cancer, as was most likely in this case; other cancers frequently found in patients with nonbacterial thrombotic endocarditis include lung, colon, and prostate cancers. The thrombophilia associated with malignant disease is thought to play an important role in the formation of valvular lesions; in a series of autopsy-proven cases of nonbacterial thrombotic endocarditis, disseminated intravascular coagulation was present in 71% of the cases. Although the laboratory findings in this patient were not typical of those associated with a consumptive coagulopathy, such as the presence of schistocytes, elevated clotting times, low fibrinogen levels, and low platelet levels, the pulmonary embolus and the venous thrombi in the legs were consistent with a hypercoaguable state induced by malignant disease.
The pathophysiology of nonbacterial thrombotic endocarditis is not well understood. Damage to the valvular endothelium is considered to be a critical first step in its pathogenesis, and patients with rheumatic or congenital heart disease are at elevated risk. Endothelial damage may be the result of high blood flow, direct trauma, immune-complex deposition, or complement activation, or it may be an elaboration of interleukin-1, interleukin-6, and tumor necrosis factor by tumor cells. The underlying thrombogenicsurface then acts as a nidus for platelet aggregation and fibrin deposition and leads to the formation of small verrucae, most of which are less than 3 mm in diameter.The valvular lesions of nonbacterial thrombotic endocarditis are usually present on the atrial surface of the mitral valve or on the ventricular surface of the aortic valve, at the point of valve coaptation. These lesions embolize frequently; the spleen, kidney, brain, and heart are the most frequently affected organs.
Current guidelines suggest that patients with nonbacterial thrombotic endocarditis and thromboembolism should be treated with full-dose heparin.As in the management of venous thromboembolism in patients with cancer, warfarin is less effective than heparin(unfractionated or low-molecular-weight) in the treatment of nonbacterial thrombotic endocarditis.Treatment of the underlying cause of the endocarditis is most likely to lead to a cure. Unfortunately, as in the present case, nonbacterial thrombotic endocarditis is often a sign of widely disseminated cancer and carries a poor prognosis.
There are no pathognomonic features in nonbacterial thrombotic endocarditis. Fever, cardiac murmur, leukocytosis, and elevated levels of C-reactive protein are present less frequently in patients with nonbacterial thrombotic endocarditis than in those with infective endocarditis. In this case, the final diagnosis of nonbacterial thrombotic endocarditis with underlying adenocarcinoma was established only after a thorough search for a cause of both the arterial and the venous thromboses.


@NEJM